Copergrine

Copergrine EMR · AI-Powered EHR & Practice Management Software

AI-powered EMR and practice management software.

Bring clinical documentation, scheduling, e-prescribing, billing, and patient communication into one system. Support in-person and telehealth visits with AI-assisted notes and built-in checks that help your team identify billing issues before claim submission.

14-day trial · Medical Practice EMR $229 per provider seat first 6 mo · $380 after, $499one-time setup · Home Health and Therapy & Behavioral Health billed per Medicare number, unlimited clinicians

An Asian-American physician at her modern office desk working entirely on a laptop with the EMR dashboard — no paper anywhere
Copergrine EMR dashboard

The same EMR dashboard your clinicians sign into — whether they bill Tele & Health or Home Health visits.

Two clinical models · one platform

Pick what you actually bill.

Medical Practice EMR

Power your in-clinic and telehealth practice with one platform.

An EMR first — same-day scheduling, encounter charting with an AI scribe, e-prescribing including controlled substances, clean insurance claim submission, cash-pay checkout, branded patient portal. Telehealth visits use the same chart and same workflow as your in-person visits — it's a channel, not a separate product.

  • AI scribe drafts; the licensed provider signs
  • Built-in clearinghouse — Medicare, Medicaid, commercial
  • EPCS-ready e-prescribing
  • Custom-domain patient portal (portal.yourpractice.com)
  • Card-on-file + cash-pay checkout
  • Same-day appointment booking widget for your site

Home Health & Therapy

For Medicare-certified Home Health Agencies.

Referral intake, OASIS assessments, multi-discipline plans of care, EVV-tracked visits, PDGM grouping, iQIES export, and clean 837I claim submission. Built for the full agency workflow — PT, OT, SLP, RN, MSW, and HHA disciplines under one roof.

  • OASIS-E SOC, ROC, RECERT, DC + iQIES submission
  • EVV — visit-time integrity per CMS / state mandate
  • PDGM grouping + 30-day period billing
  • Multi-discipline: PT, OT, SLP, RN, MSW, HHA
  • Supervising-provider workflow with co-sign queue
  • clean 837I claims to Medicare + commercial

Running both? You pick “Both” at signup. One organization, one billing account, providers licensed per line. See how the math works →

Occupational health

DOT / CDL physicals, start to certificate

Certified examiners document the MCSA-5875, record the federal determination, and issue the MCSA-5876 certificate from the chart. The worklist tracks determinations pending, certificates expiring, and the National Registry reporting deadline.

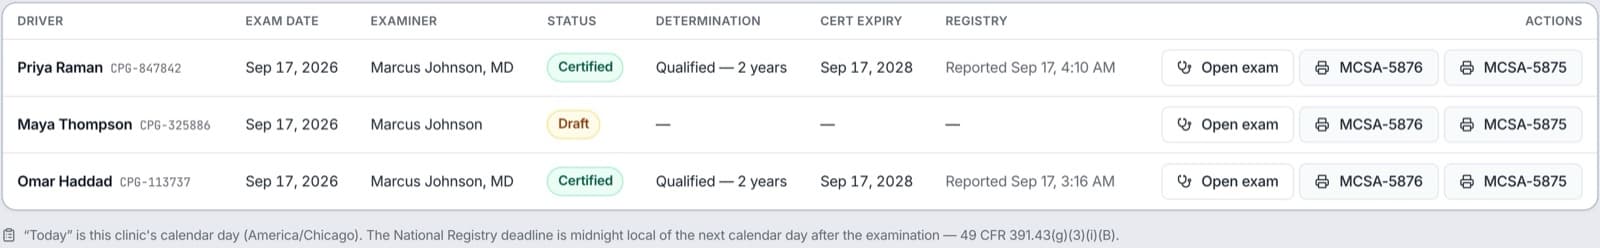
The DOT exams worklist for a demo clinic — three drivers examined today, each row showing the examiner, status (Certified or Draft), determination, certificate expiry, the National Registry report timestamp, and buttons to open the exam or print the MCSA-5876 and MCSA-5875

The DOT worklist

Every driver examined today with status, determination, certificate expiry and the registry report on one row.

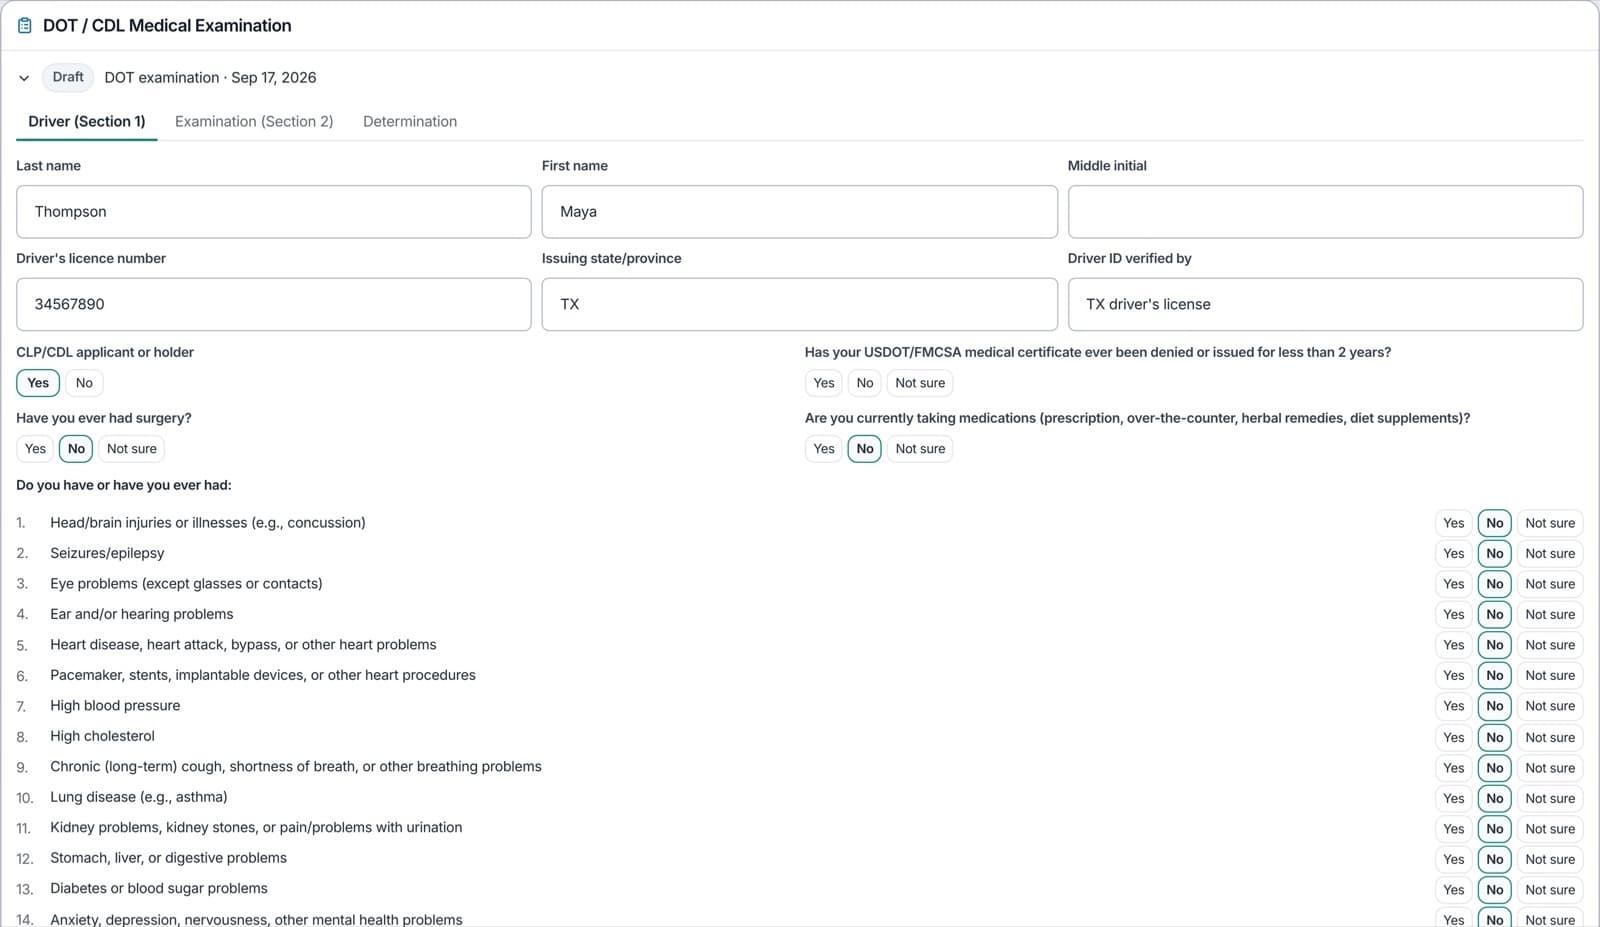
Section 1 of the DOT examination in the chart — the driver's licence details, CLP/CDL status, and the health-history questions answered Yes, No or Not sure one row at a time

Driver history, Section 1

The MCSA-5875 driver section captured as answers, not a scanned form.

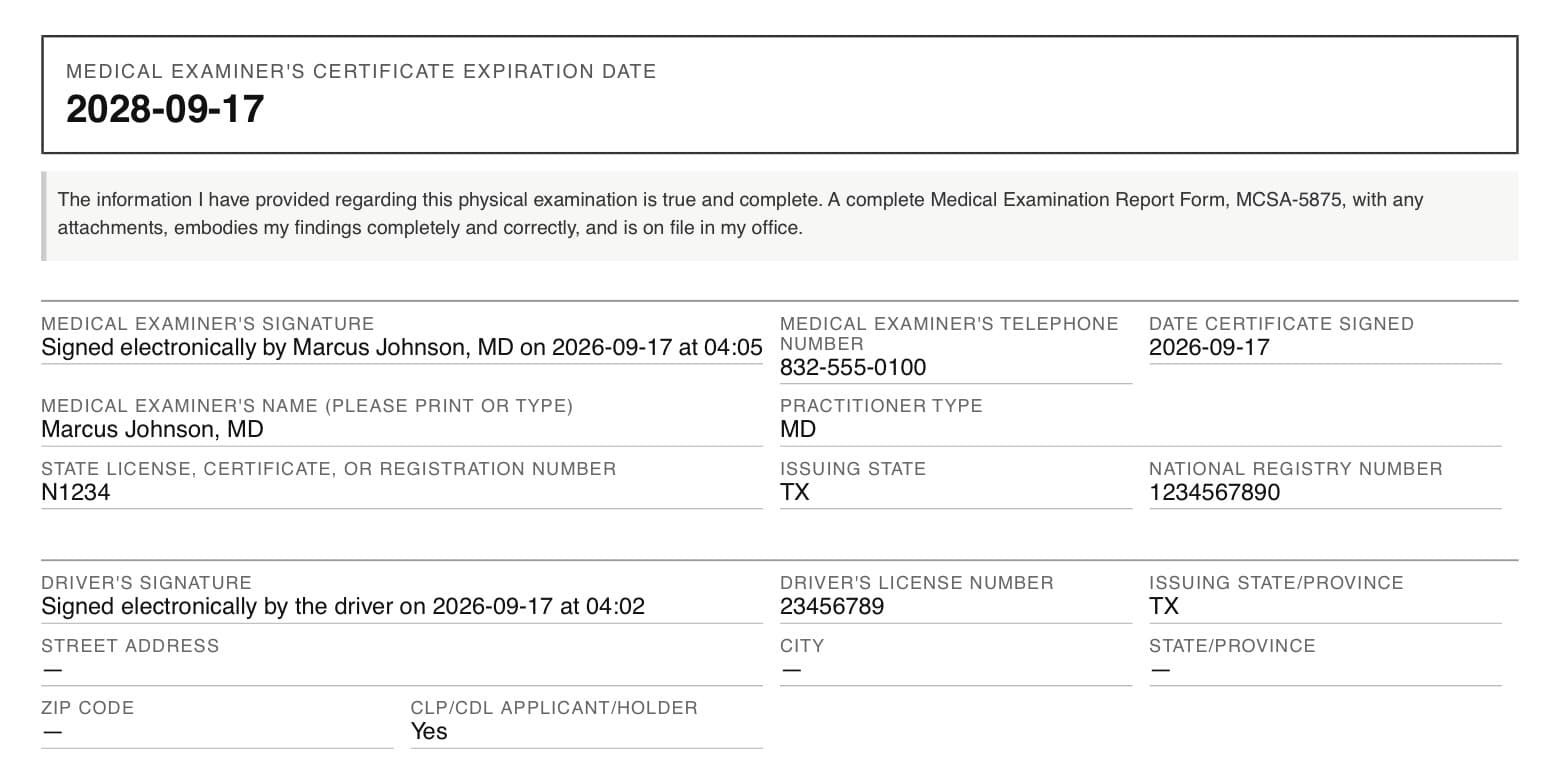
The lower half of a signed Medical Examiner's Certificate, form MCSA-5876, issued from the chart — the certificate expiration date, the examiner's electronic signature, name, state licence, issuing state and National Registry number, and the driver's electronic signature and licence

MCSA-5876 certificate

Issued from the chart once the examiner records the determination.

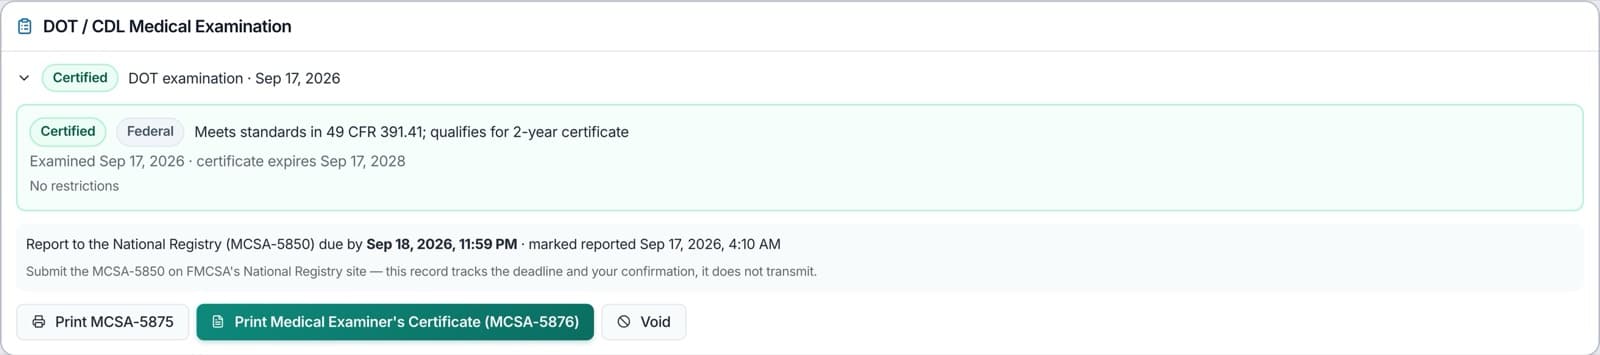
A certified DOT examination summarised in the chart — Certified badge, the federal determination that the driver meets the 49 CFR 391.41 standards and qualifies for a 2-year certificate, the expiry date, the National Registry MCSA-5850 reporting deadline marked reported, and buttons to print the MCSA-5875 and the certificate

The determination, on the chart

Certified, expiry date and the National Registry reporting deadline tracked against the exam.

The profitability difference

Most denials are preventable. Copergrine stops them before the claim leaves.

Other systems help you workdenials after a payer sends them back, weeks later, as lost time and delayed cash. Copergrine's proprietary billing engine catches the causes of denials at the encounter, so cleaner claims go out the first time and you keep more of what you bill.

Checked before a claim is ever transmitted

  • Real-time insurance eligibility (270/271) at scheduling and check-in
  • Medicare NCCI (PTP) and MUE edits: the bundling and unit limits most small-practice EMRs skip
  • CPT / ICD / modifier / units validated against the live code catalog
  • Place-of-service and telehealth-modifier compliance
  • Prior-authorization holds and timely-filing enforcement
  • A guardrail that prices every claim from the encounter and never fabricates a charge
  • An owner/admin review gate that blocks any claim carrying a denial-causing defect

What that means for your practice

  • Fewer denials: defects are flagged at the encounter, not discovered weeks later.
  • Faster, cleaner payment: first-pass claims mean less rework and quicker cash.
  • More collected revenue: fewer write-offs and timely-filing losses on money you already earned.
  • Compliance, inline: HIPAA- and SOC 2-aligned checks run with billing, not as a separate audit.

Eligibility, scrubbing, prior-auth, and remittance are built into every seat. No separate clearinghouse fees, no per-feature add-ons.

One platform underneath

The hard parts that every clinical practice needs — built once.

AI drafts. Humans sign.

The AI scribe and coding assistant draft notes, ICD/CPT codes, and care-plan language. Licensed clinicians review and sign. Every accepted suggestion is auditable.

Evidence-based Clinical Library

Confirm a diagnosis and Copergrine surfaces a guideline-anchored treatment plan — citing the society, guideline, and year — curated by our clinical team from leading medical societies (ADA, AHA/ACC, AACE, USPSTF, IDSA, AAFP, ACOG, AAP, and more). You decide how it applies to the patient; you sign.

Built-in clearinghouse

Production-active. 837P + 837I, 270/271 eligibility, 277CA acknowledgments, 835 ERAs. No portal scraping, no third-party seat fees.

Tenant isolation

Postgres Row-Level Security on every PHI table. Defense-in-depth audited at 9 layers. Cross-tenant queries fail closed.

Compliance Wizard

10-step credentialing flow: NPI verification, state license, DEA, CAQH, payer enrollment status. Aegis tracks every artifact.

Patient experience

Passwordless magic-link portal, encrypted visit-summary PDFs, push notifications on your own domain. No third-party messaging vendors.

Multi-org single sign-on

A clinician who works for both your clinic and an affiliated HHA signs in once and switches with one click. Per-org role overrides; per-org audit.

Honest pricing

Two ways to pay.
Both of them published.

Medical Practice EMR is licensed by the provider seat: $229 per provider seat per month for your first 6 months, then $380 per month thereafter. Medical groups can instead license concurrent clinical licenses: For first-time clients, $1,500 per month includes 5 concurrent clinical licenses and each additional concurrent license is $285 per month for the first 6 months; then $2,000 per month includes 5 concurrent clinical licenses, and each additional concurrent license is $380 per month, with unlimited locations. Every clinician keeps an individual account. Group is billed monthly. A one-time $499 setup fee covers onboarding, data-migration assistance, and payer-enrollment support. It is waived in full on annual prepay. Admin, billing, nursing, and front-desk staff seats are free under your headcount cap.Home Health and Therapy & Behavioral Health are licensed by the Medicare number instead — one unit per CCN or PTAN, stepped by the active census on it, with unlimited clinicians and staff.

Your accepted Medical Practice EMR rate schedule, including the 6-month introductory-to-standard step, is protected for 24 calendar months. Adding or removing licenses still changes your total. It is not a 24-month commitment, and your rates do not increase automatically when the protection period ends. No long-term commitment on monthly plans: there is no minimum term, and cancellation takes effect at the end of the current billing period. The Master Subscription Agreement and Business Associate Agreement still govern.

Medical Practice EMR

Licensed by the provider seat, or by concurrent license for medical groups

$229 per provider seat first 6 mo · $380 after

Admin, billing, nursing, and front-desk staff seats are free under your headcount cap.

Home Health

Licensed by the Medicare number (CCN)

From $490 first 6 mo · from $690 after, per Medicare number (CCN) at 1–15 patients

Unlimited clinicians and staff — headcount is not a price input.

Therapy & Behavioral Health

Licensed by the Medicare enrollment (PTAN)

From $229 first 6 mo · from $380 after, per Medicare enrollment (PTAN) at 1–30 clients

Unlimited clinicians and staff — headcount is not a price input.

See the full pricing page →

Comparing EMRs? See how Copergrine stacks up against Axxess, WellSky, Tebra, SimplePractice, and the legacy enterprise EMRs.

Frequently asked questions

Copergrine EMR, in plain terms

What is Copergrine EMR?+

An EMR for both telehealth and in-person care, built for private practices, urgent care, medical clinics, and wellness clinics. It includes charting, e-prescribing, scheduling, labs and imaging, an AI clinical scribe, denial-prevention billing, and an evidence-based Clinical Library — on one HIPAA-compliant, multi-tenant platform. Copergrine drafts; your licensed clinician reviews and signs.

Is Copergrine an EMR for in-person visits or only telehealth?+

Both. In-person and telehealth are first-class visit types — multi-location scheduling, in-clinic and video documentation, and billing for each. Telehealth is a channel, not the whole product.

What is the Copergrine Clinical Library?+

When a clinician confirms a diagnosis, Copergrine surfaces a guideline-anchored treatment plan citing the society, guideline, and year — curated and validated by our clinical team from leading medical societies including ADA, AHA/ACC, AACE, USPSTF, IDSA, AAFP, ACOG, and AAP, with more added over time. It is clinical decision support: every line is editable, and the clinician decides how it applies and signs.

How does Copergrine help prevent claim denials and delayed payments?+

With compliance-first billing: real-time insurance eligibility, claim scrubbing that validates CPT/ICD/modifier/units before submission, prior-authorization holds, timely-filing checks, automatic remittance posting and reconciliation, and a guardrail that never fabricates a charge. Costly mistakes are caught before they become denials or delayed payments.

How does Copergrine's billing engine help a practice make more money?+

By preventing denials instead of working them after the fact. Every claim is scrubbed before it transmits (real-time eligibility, Medicare NCCI/MUE edits, CPT/ICD/modifier/units validation, prior-auth holds, and timely-filing enforcement), so the causes of denials are caught at the encounter. Cleaner first-pass claims mean less rework, fewer write-offs, faster cash, and more of what you bill actually collected.

Does Copergrine check Medicare NCCI and MUE edits before claims go out?+

Yes. The billing engine validates claims against Medicare's National Correct Coding Initiative (NCCI/PTP) bundling edits and Medically Unlikely Edits (MUE) unit limits before submission, the pre-submission checks many small-practice EMRs leave to the clearinghouse or skip entirely. Catching these at the encounter prevents a common, avoidable class of denials.

What types of practices use Copergrine?+

Private practices, urgent care, medical clinics, wellness clinics, and Medicare-certified home health agencies — solo to multi-location — all on one multi-tenant platform with row-level data isolation between organizations.

Does Copergrine's AI make clinical decisions?+

No. Copergrine's AI drafts notes, suggests codes, and drafts care-plan language; a licensed clinician reviews and signs everything. Every accepted suggestion is logged and auditable.

Is Copergrine a home health EMR?+

Yes. The Home Health & Therapy line is built for Medicare-certified home health agencies and supports OASIS-E assessments, EVV (Electronic Visit Verification) with geo-stamped check-in and check-out, PDGM billing, 485 plan-of-care management, and clean-837I claim submission. State EVV aggregator submission is built and is switched on state by state, only after the agency's aggregator credentialing for that state is approved — confirm your state's status with us before you rely on it. It runs on the same multi-tenant platform as Copergrine EMR.

What does the home health EMR pricing look like?+

The Home Health & Therapy line is licensed by the Medicare number, not by headcount: one unit per CCN, stepped by the active patient census on that number. From $490 per Medicare number (CCN) per month for your first 6 months at 1–15 patients, stepped by active patient census; from $690 per month thereafter. Unlimited clinicians and staff — headcount is not a price input. OASIS-E, EVV and PDGM billing are included — not add-ons. See /emr/pricing for the full band table.